Happy Michigan Indian Day: A Snapshot of Michigan Tribes Exercising Sovereignty

Today is Michigan Indian Day, designated by Michigan law as the fourth Friday of every September.

In honor of the day, I’m offering a snapshot of what Tribal sovereignty looks like in Michigan. It includes:

Land Back • Treaty Rights • Citizenship • Education • Child Welfare • Health Care • Policing • Courts • Utilities • Economic Regulation • Manoomin • Culturally Grounded Governance

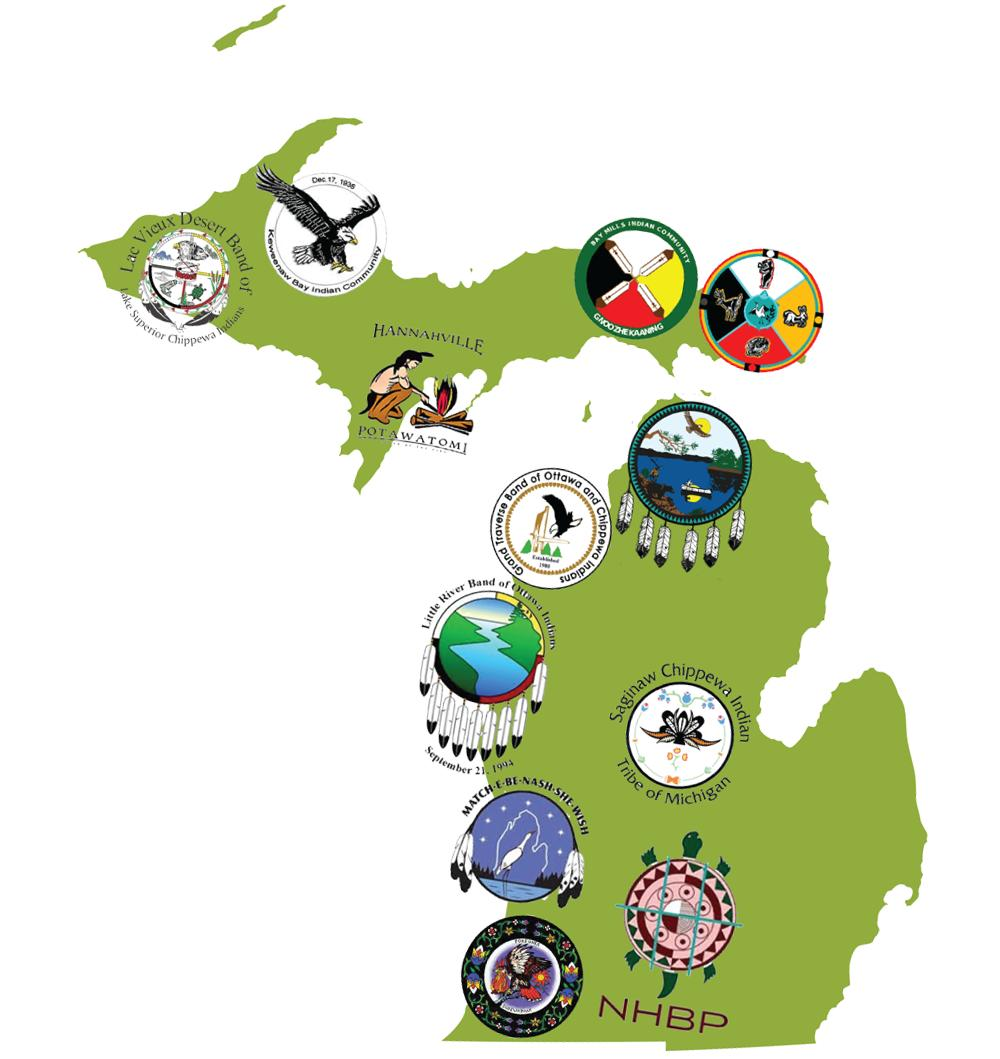
Below are 12 recent examples, one drawn from each Michigan Tribe.

It looks like bringing ancestral land home, and deciding what happens next. At the end of 2024, 188 acres along West Grand Traverse Bay were returned to the Grand Traverse Band of Ottawa and Chippewa Indians. GTB named the land Mashkiigaki, “place of the medicines,” reflecting its significance for hunting, fishing, gathering, medicines, wetlands, and coastal habitat. Since then, GTB has begun reconnecting Tribal citizens with the land and laying the groundwork for ecocultural restoration. The Tribe has surveyed citizens about their memories and aspirations for Mashkiigaki, initiated bird and invasive species surveys, planned a study of creek and wetland hydrology, and begun mapping sensitive habitat and possible public access routes. In 2026, GTB received approximately $1.3 million from NOAA, part of the federal grant approved in 2024, to support restoration and community engagement at Mashkiigaki. The planning remains Tribal-led, with elders, citizens, and government staff helping determine the land’s future. GTB’s announcement on the return of Mashkiigaki

It looks like leading a fight to protect treaty-protected waters. Bay Mills Indian Community has been a central leader in the Tribal campaign against both the existing Line 5 dual pipelines and Enbridge’s proposed tunnel beneath the Straits of Mackinac. Its opposition is grounded in the 1836 Treaty of Washington, treaty-protected fishing and gathering rights, and the Tribe’s sovereign responsibility to protect Michilimackinac, a sacred place at the heart of Anishinaabe creation traditions. Bay Mills formally called for Line 5’s decommissioning in March 2015, supported Michigan’s 2020 revocation and termination of Enbridge’s 1953 easement, and in 2021 formally banished Line 5 from Tribal lands, including the Straits. The Tribe also helped bring the dispute before the U.N. Permanent Forum on Indigenous Issues, which in 2023 recommended that the United States and Canada decommission Line 5. In litigation over the existing crossing, Bay Mills filed amicus briefs supporting the State’s efforts to keep its shutdown cases in state court, including a 2023 Sixth Circuit brief in Nessel v. Enbridge on behalf of a coalition that NARF describes as more than 60 Tribal Nations and First Nations.

Bay Mills has simultaneously challenged the proposed tunnel before the Michigan Public Service Commission, EGLE, the Michigan courts, and the U.S. Army Corps of Engineers. It intervened in the MPSC proceeding and introduced Tribal and expert testimony on treaty rights, fisheries, climate impacts, alternatives, and tunnel explosion risks. It also challenged EGLE’s 2021 wetlands permit and participated in the Army Corps’ federal review as a cooperating agency. In March 2025, Bay Mills and other Tribes withdrew as cooperating agencies after the Corps moved to fast-track approval under the asserted national “energy emergency.” The MPSC approved the tunnel in December 2023, and the Court of Appeals affirmed in February 2025. In July 2026, the Michigan Supreme Court vacated the MPSC’s approval. It remanded for a new analysis of the project’s environmental effects, feasible alternatives, and impacts on public trust resources (In re Application of Enbridge Energy to Replace & Relocate Line 5, No. 168335 (Mich. July 31, 2026)). EGLE had approved wetlands and bottomlands permits for the tunnel two weeks earlier. The Army Corps issued its record of decision in August notwithstanding the ruling, and Bay Mills condemned the federal decision as a breach of treaty and trust responsibilities. In September 2026, after Governor Whitmer announced that EGLE would re-review its permits, Bay Mills and three other Tribal Nations petitioned for a contested case hearing to overturn them. Bay Mills’ Line 5 information portal Michigan Supreme Court decision

It looks like deciding who belongs to the political community. In March 2026, Hannahville Indian Community amended its Tribal Enrollment Ordinance, governing membership applications, the Enrollment Committee, appeals, records, relinquishment, and loss of membership. Few exercises of governmental authority are more foundational than determining the citizenship of the political community. Hannahville’s 2026 Tribal Enrollment Ordinance

It looks like reshaping a regional education system. Keweenaw Bay Indian Community is leading a five-year Promise Neighborhood covering the L’Anse Reservation and surrounding Baraga County. The cradle-to-career initiative links local schools with early childhood, family, college, and career supports; KBIC cultural advocates and Ojibwe language instructors also work with area schools to bring Ojibwe language, history, and culture into classrooms. KBIC Promise Neighborhoods U.S. Department of Education project profile

It looks like exercising responsibility for Tribal children under Tribal law. The Saginaw Chippewa Indian Tribe governs child protection through its own Children’s Code and institutions. Tribal law provides for Children’s Court jurisdiction, child protection proceedings, foster care and child care regulation, adoption, and other matters affecting Tribal children, while Anishnaabeg Child and Family Services carries out child and family services within that Tribal governmental and legal framework. Saginaw Chippewa Children’s Code Anishnaabeg Child and Family Services

It looks like building a health system across the Upper Peninsula. The Sault Ste. Marie Tribe of Chippewa Indians operates nine health clinics or centers across its 7-county service area, providing varying combinations of medical, dental, behavioral health, pharmacy, and other services. Earlier this week, the Tribe broke ground on a major expansion and renovation of its Sault Health Center, designed to improve patient care while maintaining connections to Anishinaabe spiritual and cultural beliefs. Sault Tribe Health Division September 22 groundbreaking announcement

It looks like making jurisdiction work across borders. In October 2025, the City of Petoskey formally swore in Little Traverse Bay Bands of Odawa Indians Tribal Police under a cross-deputization arrangement allowing LTBB officers to assist within city jurisdiction. Petoskey officers, in turn, were to be sworn in by LTBB so they could respond where the Tribe has primary jurisdiction. The arrangement is especially striking given that shortly after LTBB’s federal reaffirmation, local officials once accused its officers of “impersonating police officers.” Today, Tribal and local governments extend law enforcement authority to one another. Petoskey Department of Public Safety 2025 Annual Report Frank Ettawageshik recounts LTBB’s earlier cross-deputization history

It looks like a Tribal court telling another branch of Tribal government what the Constitution requires. In Romanelli v. Tribal Council, the Little River Band of Ottawa Indians Tribal Court ruled in May that the Ogema’s proposed FY2026 budget had become the Tribal budget by operation of the Constitution and issued a writ of mandamus requiring the Tribal Council to appropriate the funds. That’s Tribal constitutional law in action, with a Tribal judiciary resolving a separation of powers dispute within Tribal government. Romanelli v. Tribal Council order

It looks like making sure the drinking water is safe and the sewer system works. In March, the Match-E-Be-Nash-She-Wish Band of Pottawatomi Indians (Gun Lake Tribe) enacted a new Water and Sewer Act. The law creates a Tribal regulatory system covering utility connections, permits, inspections, industrial discharges, water use restrictions, enforcement, fines, and Tribal Court proceedings. Sometimes sovereignty looks like constitutional litigation, and sometimes it looks like the sewer code. Gun Lake Tribe Water and Sewer Act

It looks like regulating a new market, and mobilizing government to protect citizens. In 2025, the Lac Vieux Desert Band of Lake Superior Chippewa Indians entered a Tribal-State cannabis compact allowing a Tribally regulated cannabis business to participate in Michigan’s regulated market. Then, in January, amid concerns about ICE activity affecting Native people, the Tribal Council issued formal guidance to citizens, waived fees for replacement Tribal IDs, and directed citizens to Tribal enrollment, law enforcement, leadership, and legal offices for assistance. LVD–Michigan cannabis agreement LVD Tribal Council statement regarding ICE activity

It looks like making law for a relative rather than merely regulating a commodity. In September 2025, the Nottawaseppi Huron Band of the Potawatomi enacted a Mnomen (Wild Rice) Code. The law recognizes Mnomen as the Tribe’s official grain and a protected Tribal resource, creates a Mnomen Wgema composed of Tribal citizens, regulates harvesting and transplantation, authorizes enforcement by Tribal conservation officers, and provides penalties for violations. The Code also recognizes Mnomen as a living spirit, medicine, and part of the Tribe’s migration story. Environmental regulation, cultural responsibility, and Indigenous law operate here in the same legal framework. NHBP Mnomen (Wild Rice) Code

It looks like designing governmental institutions on Indigenous terms. Under the Pokagon Band of Potawatomi Indians’ Elders Council Code, the Elders Council is a governmental instrumentality that provides guidance to the membership and to the Band’s legislative, executive, and judicial institutions on matters of history, traditions, and culture. Pokagon law also permits one of the seven Tribal Council seats to be held by an Elders Council representative, who carries all the rights and responsibilities of a Tribal Councilperson. Pokagon Elders Council Code, current through May 2026

Every day across the state, each of Michigan’s 12 Tribes exercises governmental authority over lands, resources, institutions, services, and citizens.


Tribal Innovations: Gila River Builds a Pathway to Medical Practice Within Its Health System

Gila River Health Care has committed more than $25 million through 2034 to establish a University of Arizona medical school branch within the Gila River Indian Community’s tribally operated health system. The investment will support faculty, educational infrastructure, and full tuition scholarships for students.

Beginning in July 2027, the branch plans to admit ten students each year to a three-year primary care MD program. Students will spend their first 18 months in Phoenix, then move to Sacaton, thirty-two miles southeast of Phoenix, for 18 months of clinical education within Gila River Health Care.

This goes beyond hosting a short clinical rotation. Gila River is funding a medical school branch where students will complete half of their training while caring for patients in a Tribal health system.

The joint announcement is here.

Additional Resources

Matthew Tobey, MD, et al., Graduate Medical Education in Indian Country: Addressing Workforce Shortages and Improving Health Outcomes, National Academy of Medicine Perspectives (Aug. 11, 2025)

Click the image above to watch a 2.5 minute video on this initiative.

Tribal Consultation Today: What Would 340B Rebates Mean for Tribal Clinics?

HRSA is testing a change that could require Tribal health clinics to pay more upfront for certain prescription drugs, then claim their 340B discount afterward. This is the agency’s second attempt, since a federal district court vacated HRSA’s earlier pilot notice on February 10, 2026, and HRSA withdrew it before issuing a revised version in August.

340B is a federal program that lets eligible health providers buy outpatient drugs at reduced prices. HRSA, the federal Health Resources and Services Administration, runs the program.

For example, suppose a clinic’s 340B price for a medicine is $60, while its price without that discount is $100. The clinic ordinarily pays $60 when it buys the medicine. Under the pilot, it could pay $100 first, submit information about the drug it provided, and receive the $40 difference later as a rebate.

The pilot could apply to certain drugs selected for Medicare price negotiation in 2026 and 2027. Being on that list doesn’t automatically put a drug in the pilot; HRSA must approve the manufacturer’s plan. The eligible drugs include medicines for:

  • Diabetes and weight management, such as Jardiance, Ozempic, and Wegovy.
  • Heart conditions and blood clots, such as Entresto and Eliquis.
  • Asthma and chronic lung disease, such as Breo Ellipta and Trelegy Ellipta.
  • Cancer, such as Ibrance and Xtandi.

For an affected clinic, the question is how it pays the higher purchase price while waiting for the rebate, and how much work it takes to obtain it. HRSA’s rules would give clinics at least 45 days after dispensing to submit the required data. A manufacturer would then have 10 calendar days after a complete submission to pay the rebate or provide a documented denial. If information is missing, that 10-day clock starts over when the submission is completed. HRSA’s pilot notice; Medicare’s selected drug lists.

The National Council of Urban Indian Health (NCUIH) estimates that under the rebate model, the cash outlay for urban Indian organization 340B participants could rise by as much as $342,716 a year for clinics that, in NCUIH’s words, “operate with limited cash reserves and narrow margins that leave little capacity to absorb delayed rebate payments.” NCUIH has shared an information sheet explaining its position that Indian health care providers should be exempted from the pilot. A link to the information sheet is below.

HRSA is consulting Tribal leaders today, September 16, from 3–5 p.m. ET, about how the pilot would affect Tribal health programs and whether its payment and reporting procedures are workable. Written comments are due October 1. The consultation invitation includes the registration link and address for comments. Approved manufacturer plans are scheduled to take effect January 1, 2027.

Participant Information:
What: HRSA Tribal Consultation on the 340B Rebate Model Pilot Program
Date: Wednesday, September 16, 2026
Location: Virtual (Zoom)
Time: 3:00 – 5:00pm ET
Registration link: Consultation Registration – Zoom

If you’re unable to attend, you’re encouraged to send any written testimony or comments to tribalconsultation@hrsa.gov by Thursday, October 1, 2026.

For more information, please contact Commander Sharyl Trail, Director of the HRSA Office of Tribal Affairs at strail@hrsa.gov.

Additional Resource

National Council of Urban Indian Health Policy Update: HRSA to Hold Tribal Consultation on 340B Rebate Model Pilot Program

NCUIH: The Need to Exempt Indian Health Care Providers from HRSA’s 340B Rebate Model Pilot

Neoshia Roemer on Indian Child Welfare and Public Health

Neoshia Roemer has published “Kill the Nation, Save the Child” in the Houston Journal of Health Law & Policy.

Here is the abstract:

At the opening of the Carlisle Indian School in 1879, Richard Henry Pratt remarked that Indian boarding schools were necessary to “kill the Indian…and save the man.” In the 150 years since, removing American Indian children from their tribal communities has become a staple in the settler colonial project through the boarding school project, Indian adoptions, and the state-run family regulation system. In 1978, Congress attempted a course correct by enacting the Indian Child Welfare Act (“ICWA”) which extended protections to parents of Indian children and vested Indian Tribes with a legal interest in their member children. Aimed at protecting the best interests of the Indian child, ICWA has been under attack in recent years. As ICWA is applied in state courts around the country daily, American Indian children continue to be removed from their families at disproportionately high rates. This Article contextualizes the ongoing need for ICWA and argues that Indian child removal is a matter of Tribal public health. Removing Indian children has long negatively impacted tribal public health and continues to do so today. By removing the Indian child from their community to “save” them, settler colonialism’s goal was to eradicate the Tribal Nation. As such, this Article argues that Indian child welfare must be treated as a Tribal public health concern and resourced as such—with Tribes leading the way to provide the services their children and families need.

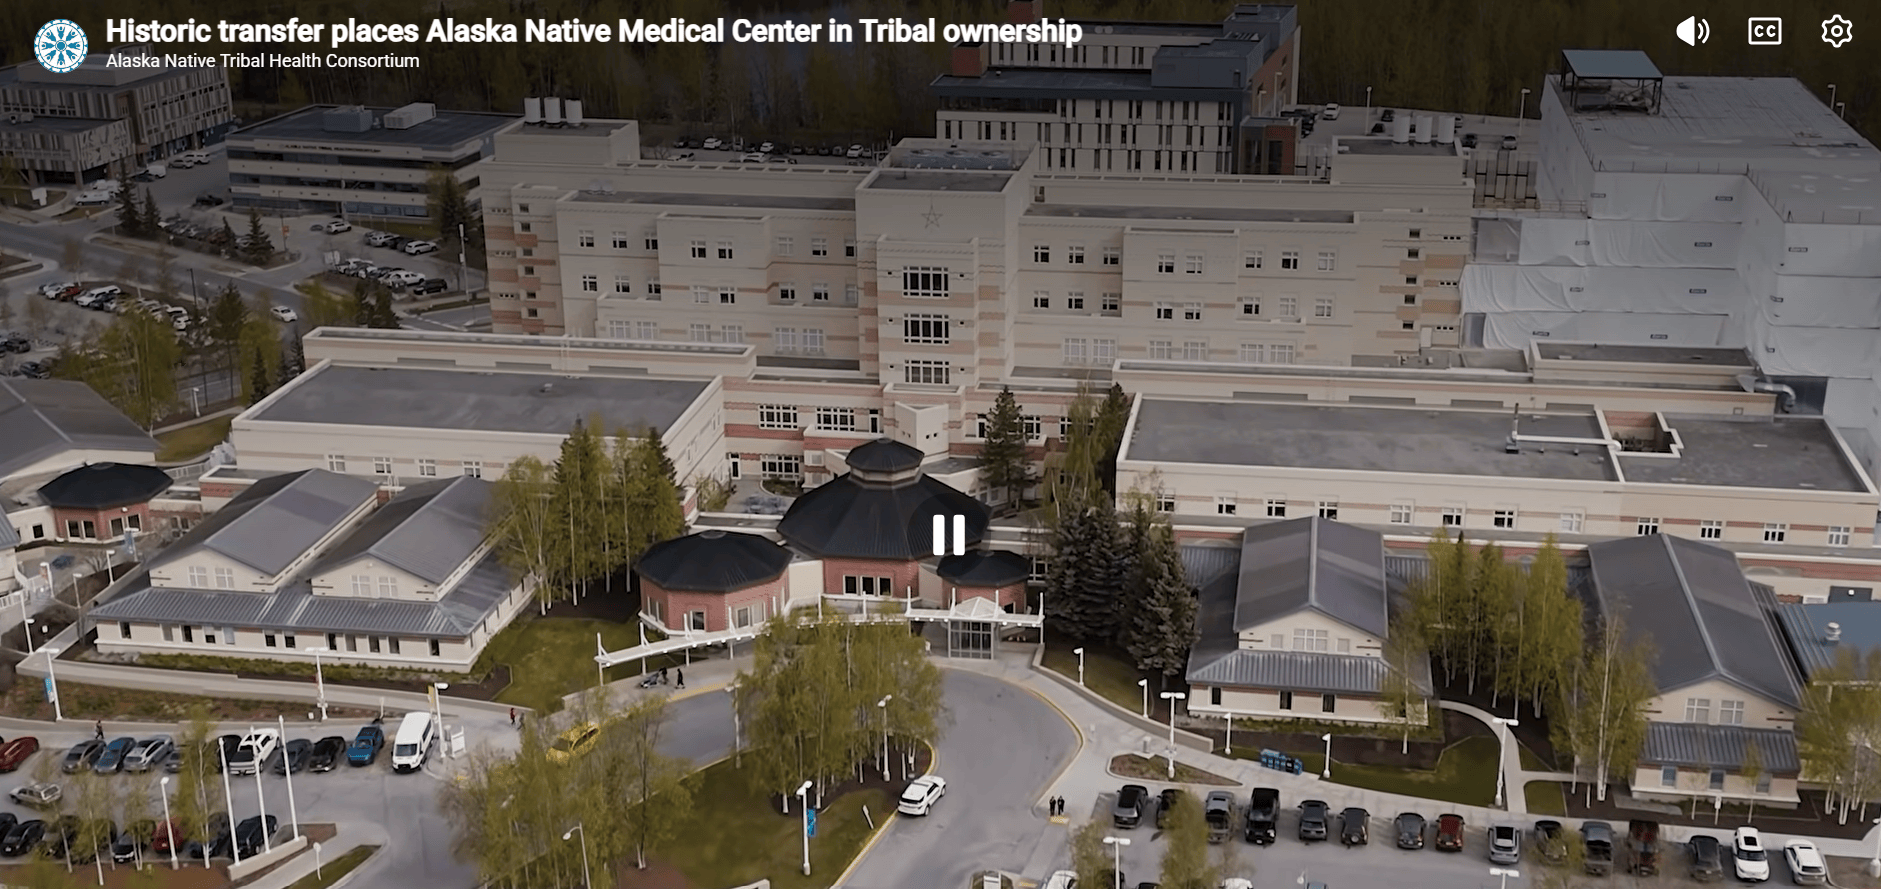
Alaska Native Tribes Now Own the Hospital They’ve Operated for Decades

For nearly three decades, Tribal organizations have operated the programs and services of the Alaska Native Medical Center, but the federal government owned the hospital building. That mismatch ended on August 24, 2026, when IHS transferred the facility to the Alaska Native Tribal Health Consortium (ANTHC) after decades of advocacy by Alaska Tribal leaders.

The transfer places the hospital itself under the control of the Tribal health system responsible for governing, operating, and investing in it. Ownership also gives ANTHC new tools to pursue federal facility-cost funding and other financing for maintenance and modernization, an important shift for a hospital in which ANTHC has already approved more than $462 million in investment. With the transfer, patient eligibility, services, employment, and current operational roles will continue as before, but now in a physical institution owned by ANTHC.

Click the image above to watch ANTHC’s video announcement of the transfer of the Alaska Native Medical Center to Tribal ownership.

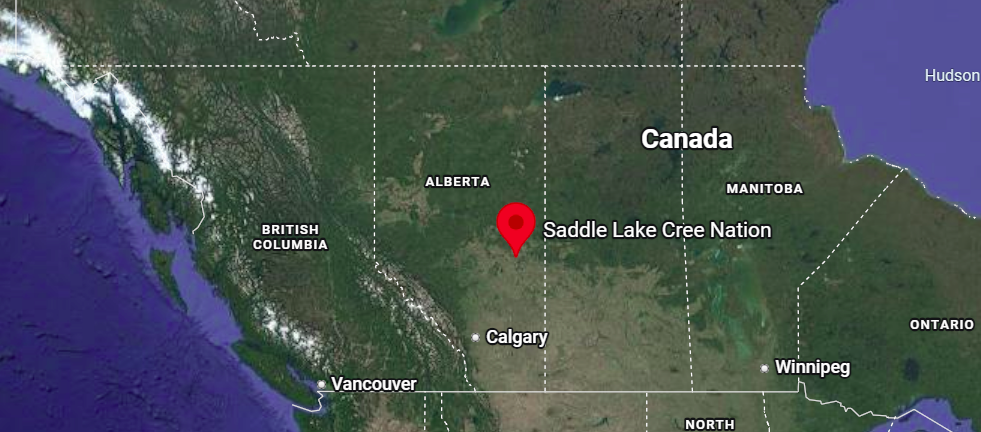
Saddle Lake Cree Nation in Alberta Invokes Treaty 6 to Protect Gender-Affirming Care

Alberta has restricted access to puberty blockers and hormone therapy for transgender youth, and it’s invoked a provision of the Canadian Constitution called the “notwithstanding clause” that allows governments temporarily to override certain constitutional rights. Saddle Lake Cree Nation is responding with reliance on Treaty 6, a source of authority that Alberta can’t override with the clause.

On September 9, during a gathering marking Treaty 6’s 150th anniversary, Chief Dale Steinhauer announced that Saddle Lake would assert its inherent and treaty-protected authority to provide gender-affirming health care on its reserve lands. The Nation is working to recruit clinicians and raise funds for legal defense and to develop its own health law.

“No longer will our children and families have their rights taken away,” Steinhauer said. “When one group’s rights are removed, we are all affected.”

Saddle Lake is grounding its position partly in Treaty 6’s “medicine chest” clause. First Nations have long understood the clause as a continuing commitment to provide comprehensive health care, not a promise frozen around the contents of a nineteenth-century medicine box.

In an interlocutory ruling in Wuskwi Sipihk Cree Nation v. Canada, a Federal Court prothonotary concluded that the First Nations’ claim could proceed and observed that, understood in its contemporary context, the medicine chest clause “may well require a full range of contemporary medical services.” The court did not finally decide the scope of that right, and the question remains unsettled.

Alberta prohibits regulated health professionals from prescribing puberty blockers or hormone therapy to patients under 16 for treating gender dysphoria or gender incongruence, subject to limited exceptions. Youth ages 16 and 17 require parental or guardian consent and approval from a physician and psychologist.

Saddle Lake’s announcement doesn’t settle whether Alberta’s regulation of health professionals applies on reserve. That question implicates provincial law, treaty rights, and the Nation’s asserted inherent jurisdiction. Saddle Lake says that clinicians working under its law will be protected from professional sanctions, but that claim may be tested if provincial regulators attempt enforcement.

Saddle Lake’s actions show that Alberta can’t invoke its own authority to abandon trans and Two-Spirit children and expect a Treaty Nation to do the same.

Additional Resources

Alberta First Nation wants to set up safe haven for gender-affirming care, Lexi Freehill and Lisa Johnson for CBC News (Sept. 10, 2026)

Treaty 6, with medicine chest clause

Section 33 of the Canadian Charter of Rights and Freedoms, commonly called the “notwithstanding clause”

Section 35, Part II of the Constitution Act, 1982, “Rights of the Aboriginal Peoples of Canada”

Section 1.92(1) of the Health Professions Act, prohibiting prescriptions for minors for the purposes of hormone therapy, including puberty suppression and hormone replacement therapy for the treatment of gender dysphoria or gender incongruence except in accordance with an order of the Minister.

Alberta Ministerial Order 31/2025, detailing circumstances where access to hormone therapy, including puberty suppression and hormone replacement therapy for the treatment of gender dysphoria or gender incongruence is permitted for a minor

The Governance of Indigenous Health, Constance MacIntosh, in Joanna Erdman, Vanessa Gruben & Erin Nelson, eds., Canadian Health Law and Policy, 5th ed. (LexisNexis Canada 2017)

Tribal Innovations Update: Chickasaw Nation Begins Construction on 160-acre Health Campus

The medical campus will include twelve buildings, a hospital, an outpatient clinic, and more than twenty-three specialties.

From the Chickasaw Nation press release:

Upon completion, the facility will grow to include a nearly 2.5 million-square-foot medical campus with 140 inpatient beds and will employ more than 5,500 staff. It is expected to serve more than 100,000 First Americans in the region.

“This campus will do things most hospitals cannot. We are building medical residencies, training the next generation of doctors right here in Oklahoma, and in Newcastle,” Governor Anoatubby said. “We are building a First American research center owned and operated by a tribal nation, the first of its kind anywhere in the country.”

Chickasaw Nation Governor Chris Anoatubby, center, is joined by Chickasaw Nation elected officials and leadership staff, federal and state officials, and community leaders July 31 in groundbreaking ceremonies for the Chickasaw Nation Health Newcastle Medical Center, marking a significant investment in First American healthcare access in the Oklahoma City area.

Mark Cruz Takes Over IHS as Funding and Censorship Questions Remain

The Senate confirmed Mark Cruz (Klamath Tribes) to serve as Director of the Indian Health Service on August 7 by a 51-47 vote. His confirmation ended more than 18 months without a Senate-confirmed IHS Director following the departure of former Director Roselyn Tso in January 2025.

At his June 24 confirmation hearing before the Senate Committee on Indian Affairs, Cruz stated that he intends to advocate “ferociously” for improved health outcomes in Indian Country. The Committee’s hearing page, including Cruz’s testimony, is available here.

Cruz takes over an agency facing enormous unmet needs. Congress appropriated just over $8 billion for IHS for FY2026. By contrast, the National Indian Health Board has estimated that IHS needs approximately $76 billion to fully fund the agency and meet current needs.

Cruz will also retain his position as Senior Advisor on Tribal Health to HHS Secretary RFK, Jr. while serving as IHS Director. Holding both positions simultaneously is unusual given the size and operational responsibilities of IHS, which provides health services to about 2.8 million American Indians and Alaska Natives.

Cruz’ dual role may be particularly important to watch in light of recent changes in IHS public health communications under Secretary Kennedy. ProPublica reported last fall that IHS officials had begun flagging terms including “vaccines” and “immunizations” as risky “buzzwords” requiring additional review by agency public information officers before their use in social media updates, pamphlets, and presentations. Current and former IHS clinicians told ProPublica that the restrictions interfered with their ability to communicate effectively with patients, and one IHS doctor said that the restrictions led to her decision to leave the agency.

The ProPublica report takes on added significance in light of internal CDC emails recently made public by Sen. Bernie Sanders. The emails released in late June of this year don’t concern IHS or Cruz directly, but they document centralized HHS oversight of the CDC’s vaccine communications, including HHS direction about vaccine-related material that had been removed from CDC websites and what content would be put back online. The emails don’t establish that HHS directed the IHS restrictions reported by ProPublica, but they provide important context for Cruz’s unusual dual role, since he was already serving as Secretary Kennedy’s Senior Advisor on Tribal Health before becoming IHS Director and will now serve simultaneously in the Secretary’s office and at the head of IHS. Whether Cruz uses his new position to protect IHS clinicians’ ability to communicate evidence-based public health information is worth watching.

Pechanga Prevails in Contract Dispute with IHS

Here are the new materials in Pechanga Band of Indians v. Kennedy (C.D. Cal.):

Jaune Quick to See Smith

Prior post here.

California Federal Court Finds Pechanga Likely to Win Dispute with IHS over Denial of Opioid Treatment Facility Contract but Did Not Find Irreparable Harm

Here are materials in Pechanga Band of Indians v. Kennedy (C.D. Cal.):

Prior post here.