Here is the order in Blue Lake Rancheria v. Kalshi Inc.
Briefs here.

Here is the order in Blue Lake Rancheria v. Kalshi Inc.
Briefs here.
HRSA is testing a change that could require Tribal health clinics to pay more upfront for certain prescription drugs, then claim their 340B discount afterward. This is the agency’s second attempt, since a federal district court vacated HRSA’s earlier pilot notice on February 10, 2026, and HRSA withdrew it before issuing a revised version in August.
340B is a federal program that lets eligible health providers buy outpatient drugs at reduced prices. HRSA, the federal Health Resources and Services Administration, runs the program.
For example, suppose a clinic’s 340B price for a medicine is $60, while its price without that discount is $100. The clinic ordinarily pays $60 when it buys the medicine. Under the pilot, it could pay $100 first, submit information about the drug it provided, and receive the $40 difference later as a rebate.
The pilot could apply to certain drugs selected for Medicare price negotiation in 2026 and 2027. Being on that list doesn’t automatically put a drug in the pilot; HRSA must approve the manufacturer’s plan. The eligible drugs include medicines for:
For an affected clinic, the question is how it pays the higher purchase price while waiting for the rebate, and how much work it takes to obtain it. HRSA’s rules would give clinics at least 45 days after dispensing to submit the required data. A manufacturer would then have 10 calendar days after a complete submission to pay the rebate or provide a documented denial. If information is missing, that 10-day clock starts over when the submission is completed. HRSA’s pilot notice; Medicare’s selected drug lists.
The National Council of Urban Indian Health (NCUIH) estimates that under the rebate model, the cash outlay for urban Indian organization 340B participants could rise by as much as $342,716 a year for clinics that, in NCUIH’s words, “operate with limited cash reserves and narrow margins that leave little capacity to absorb delayed rebate payments.” NCUIH has shared an information sheet explaining its position that Indian health care providers should be exempted from the pilot. A link to the information sheet is below.
HRSA is consulting Tribal leaders today, September 16, from 3–5 p.m. ET, about how the pilot would affect Tribal health programs and whether its payment and reporting procedures are workable. Written comments are due October 1. The consultation invitation includes the registration link and address for comments. Approved manufacturer plans are scheduled to take effect January 1, 2027.
Participant Information:
What: HRSA Tribal Consultation on the 340B Rebate Model Pilot Program
Date: Wednesday, September 16, 2026
Location: Virtual (Zoom)
Time: 3:00 – 5:00pm ET
Registration link: Consultation Registration – Zoom
If you’re unable to attend, you’re encouraged to send any written testimony or comments to tribalconsultation@hrsa.gov by Thursday, October 1, 2026.
For more information, please contact Commander Sharyl Trail, Director of the HRSA Office of Tribal Affairs at strail@hrsa.gov.
Additional Resource
NCUIH: The Need to Exempt Indian Health Care Providers from HRSA’s 340B Rebate Model Pilot
*Note: I published a draft of this post this morning while I was still editing it & adding to the Tribal court slideshow. The slideshow now includes 33 images of the Tribal Justice Center construction projects currently underway or built since 2010 and included in the table below. This post is the final version. Apologies for the second post.
For decades, the Supreme Court has treated Tribal jurisdiction as a problem requiring limitation rather than governmental authority requiring respect.
The Tribal Justice construction projects below make visible something federal Indian law too often obscures: Tribal Nations are governments administering entire systems of justice. They prosecute, defend, adjudicate, supervise, treat, heal, and protect.
Below is a summary of selected Tribal court and justice center projects completed since 2010 or currently underway. Together, they range from several thousand to more than 100,000 square feet and represent well over $285 million in reported construction costs or budgets. The actual total is substantially higher because costs for many projects are not public.
None of these buildings makes Tribal justice legitimate. Tribal Nations possessed and exercised authority to govern and resolve disputes long before the United States existed, much less before anyone poured the concrete for a courthouse. These Nations are not constructing legitimacy. They are constructing the physical infrastructure through which longstanding governmental authority operates in the contemporary world.
And these justice centers don’t simply reproduce non-Indian courthouses. Many incorporate traditional peacemaking, healing and treatment programs, victim services, culturally grounded design, detention and public-safety functions, and other institutions reflecting Tribal choices about what justice should look like.
It’s worth looking at these institutions against the background of the Supreme Court’s Tribal jurisdiction cases. Again and again, the Court has approached Tribal authority through presumptions of limitation, concerns about the exercise of jurisdiction over nonmembers, and judicially created restrictions on Tribal governmental power.
Then look at the photographs and renderings. Look at the courtrooms, judges’ benches, victim services programs, treatment facilities, detention centers, peacemaking rooms, and the governmental infrastructure surrounding them. The dissonance is uncomfortable.
The problem is larger than whether particular Justices respect Tribal judges. Federal Indian law has repeatedly treated Tribal governmental authority as exceptional, where jurisdiction must be justified, bounded, divested, or subjected to limitations that would be extraordinary if imposed upon state governments.
The photographs below offer a different starting point. They show governments building the institutions through which they exercise responsibility for public safety, dispute resolution, accountability, healing, and community well-being.
So look at the photographs. Look at what Tribal Nations have built and are building. Then return to the Supreme Court’s Tribal jurisdiction cases and notice how often these governments are described primarily in terms of the authority they supposedly lack. The question shouldn’t always be whether Tribal courts have done enough to earn the nation’s confidence. Perhaps the harder question is why American law has demanded, for so long, that Tribal governments keep proving that they are governments at all.
Slideshow
| Tribe/Nation | Tribal court project | Reported cost or budget | Reported size |
|---|---|---|---|
| Cherokee Nation (OK) | New Cherokee Nation Justice Center | $40 million, full integrated Justice Center | More than 65,500 sq. ft. full integrated Justice Center |
| Muscogee (Creek) Nation (OK) | New Tribal Courthouse | $30 million cost at groundbreaking; may not be final cost at completion | 43,514 sq. ft., courthouse only |
| Quinault Indian Nation (WA) | New Tribal Courthouse | Not yet established; construction bid pending | 6,625 sq. ft., courthouse only |
| Reno-Sparks Indian Colony (NV) | Multipurpose Justice Center | Not publicly identified | 15,792 sq. ft., entire police/court/human services complex; 7,056 sq. ft., courthouse only |
| Tolowa Dee-ni’ Nation (CA) | Regional Tribal Justice Center | Federal grant and Tribal funds; total not publicly identified | Approximately 7,950 sq. ft., Justice Center addition, including court and related services |
| Cheyenne and Arapaho Tribes (OK) | Tribal Justice Center Expansion | Not publicly identified | 7,852 sq. ft. addition only; 17,072 sq. ft., entire expanded Justice Center |
| Tunica-Biloxi Tribe (LA) | Tunica-Biloxi Justice Center | Not publicly identified | Not publicly identified |
| Confederated Tribes and Bands of the Yakama Nation (WA) | Yakama Multi-Purpose Justice Center | $13,722,782, full reported project | 12,200 sq. ft., full Multi-Purpose Justice Center |
| Pokagon Band of Potawatomi Indians (MI) | Peacekeeping and Justice Center | $21.4 million, contract value for full police and court center | 30,000 sq. ft., full center, per construction manager; Tribal announcement reported 23,000 sq. ft. |
| Salt River Pima-Maricopa Indian Community (AZ) | Justice Center | $38.6 million, full court and practitioners building | 93,000 sq. ft., full Justice Center building |
| MHA Nation / Three Affiliated Tribes (ND) | Public Safety and Judicial Center | $17.2 million, Public Safety and Judicial Center building; excludes other complex phases | 29,600 sq. ft., judicial center, not including correctional facility and juvenile attending care facility |
| Ute Indian Tribe of the Uintah and Ouray Reservation (UT) | Tribal Justice Center | $38 million, full integrated court and detention center | More than 105,000 sq. ft., full integrated center |
| Gun Lake Tribe / Match-E-Be-Nash-She-Wish Band of Pottawatomi Indians (MI) | Tribal Court Building | Court building cost not separately reported from government campus project | 9,000 sq. ft., courthouse only |
| Oglala Sioux Tribe (SD) | Justice Center for the People | Approximately $42.2 million, full court, peacemaking facilities, law enforcement, and detention complex | Approximately 93,000 sq. ft., full complex |
| Puyallup Tribe of Indians (WA) | Puyallup Justice Center | $25 million, full integrated Justice Center | 82,300 sq. ft., entire courts, police, and detention facility |
| Shoshone-Bannock Tribes (ID) | Shoshone-Bannock Justice Center | Approximately $19.7 million, full Justice Center | 66,200 sq. ft., full court, police, and detention center |
An updated post is available here.
Neoshia Roemer has published “Kill the Nation, Save the Child” in the Houston Journal of Health Law & Policy.
Here is the abstract:
At the opening of the Carlisle Indian School in 1879, Richard Henry Pratt remarked that Indian boarding schools were necessary to “kill the Indian…and save the man.” In the 150 years since, removing American Indian children from their tribal communities has become a staple in the settler colonial project through the boarding school project, Indian adoptions, and the state-run family regulation system. In 1978, Congress attempted a course correct by enacting the Indian Child Welfare Act (“ICWA”) which extended protections to parents of Indian children and vested Indian Tribes with a legal interest in their member children. Aimed at protecting the best interests of the Indian child, ICWA has been under attack in recent years. As ICWA is applied in state courts around the country daily, American Indian children continue to be removed from their families at disproportionately high rates. This Article contextualizes the ongoing need for ICWA and argues that Indian child removal is a matter of Tribal public health. Removing Indian children has long negatively impacted tribal public health and continues to do so today. By removing the Indian child from their community to “save” them, settler colonialism’s goal was to eradicate the Tribal Nation. As such, this Article argues that Indian child welfare must be treated as a Tribal public health concern and resourced as such—with Tribes leading the way to provide the services their children and families need.

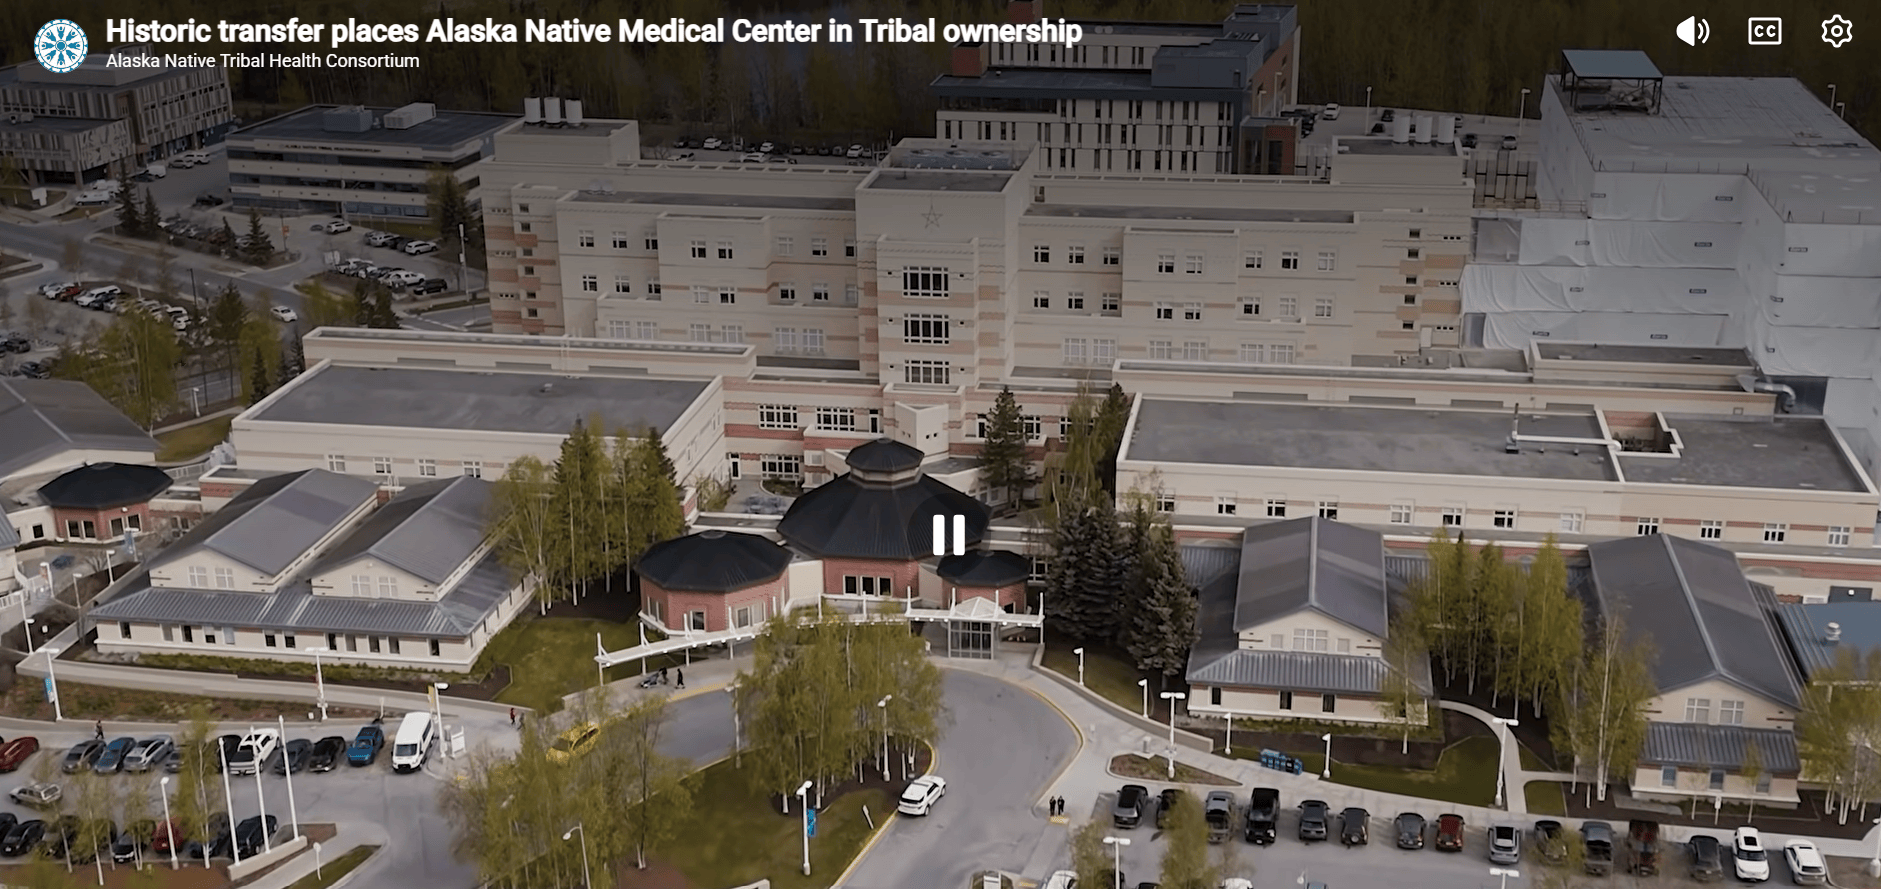
For nearly three decades, Tribal organizations have operated the programs and services of the Alaska Native Medical Center, but the federal government owned the hospital building. That mismatch ended on August 24, 2026, when IHS transferred the facility to the Alaska Native Tribal Health Consortium (ANTHC) after decades of advocacy by Alaska Tribal leaders.
The transfer places the hospital itself under the control of the Tribal health system responsible for governing, operating, and investing in it. Ownership also gives ANTHC new tools to pursue federal facility-cost funding and other financing for maintenance and modernization, an important shift for a hospital in which ANTHC has already approved more than $462 million in investment. With the transfer, patient eligibility, services, employment, and current operational roles will continue as before, but now in a physical institution owned by ANTHC.

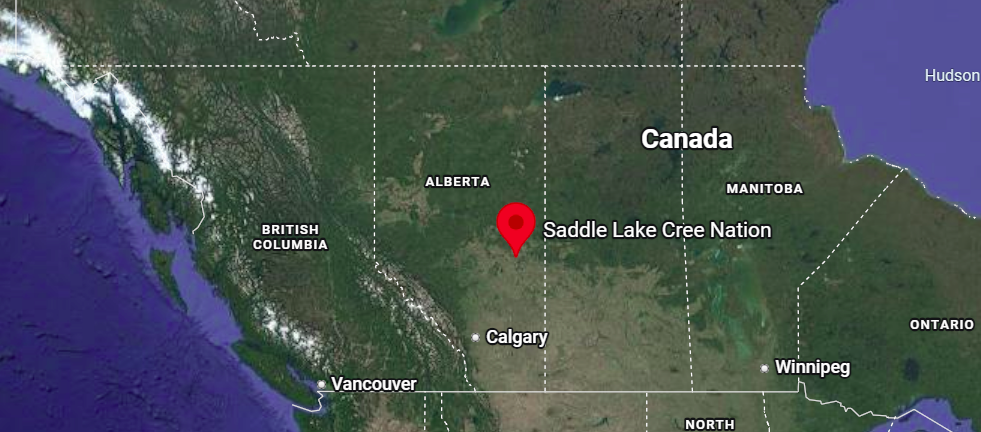
Alberta has restricted access to puberty blockers and hormone therapy for transgender youth, and it’s invoked a provision of the Canadian Constitution called the “notwithstanding clause” that allows governments temporarily to override certain constitutional rights. Saddle Lake Cree Nation is responding with reliance on Treaty 6, a source of authority that Alberta can’t override with the clause.
On September 9, during a gathering marking Treaty 6’s 150th anniversary, Chief Dale Steinhauer announced that Saddle Lake would assert its inherent and treaty-protected authority to provide gender-affirming health care on its reserve lands. The Nation is working to recruit clinicians and raise funds for legal defense and to develop its own health law.
“No longer will our children and families have their rights taken away,” Steinhauer said. “When one group’s rights are removed, we are all affected.”
Saddle Lake is grounding its position partly in Treaty 6’s “medicine chest” clause. First Nations have long understood the clause as a continuing commitment to provide comprehensive health care, not a promise frozen around the contents of a nineteenth-century medicine box.
In an interlocutory ruling in Wuskwi Sipihk Cree Nation v. Canada, a Federal Court prothonotary concluded that the First Nations’ claim could proceed and observed that, understood in its contemporary context, the medicine chest clause “may well require a full range of contemporary medical services.” The court did not finally decide the scope of that right, and the question remains unsettled.
Alberta prohibits regulated health professionals from prescribing puberty blockers or hormone therapy to patients under 16 for treating gender dysphoria or gender incongruence, subject to limited exceptions. Youth ages 16 and 17 require parental or guardian consent and approval from a physician and psychologist.
Saddle Lake’s announcement doesn’t settle whether Alberta’s regulation of health professionals applies on reserve. That question implicates provincial law, treaty rights, and the Nation’s asserted inherent jurisdiction. Saddle Lake says that clinicians working under its law will be protected from professional sanctions, but that claim may be tested if provincial regulators attempt enforcement.
Saddle Lake’s actions show that Alberta can’t invoke its own authority to abandon trans and Two-Spirit children and expect a Treaty Nation to do the same.
Additional Resources
Alberta First Nation wants to set up safe haven for gender-affirming care, Lexi Freehill and Lisa Johnson for CBC News (Sept. 10, 2026)
Treaty 6, with medicine chest clause
Section 33 of the Canadian Charter of Rights and Freedoms, commonly called the “notwithstanding clause”
Section 35, Part II of the Constitution Act, 1982, “Rights of the Aboriginal Peoples of Canada”
Section 1.92(1) of the Health Professions Act, prohibiting prescriptions for minors for the purposes of hormone therapy, including puberty suppression and hormone replacement therapy for the treatment of gender dysphoria or gender incongruence except in accordance with an order of the Minister.
Alberta Ministerial Order 31/2025, detailing circumstances where access to hormone therapy, including puberty suppression and hormone replacement therapy for the treatment of gender dysphoria or gender incongruence is permitted for a minor
The Governance of Indigenous Health, Constance MacIntosh, in Joanna Erdman, Vanessa Gruben & Erin Nelson, eds., Canadian Health Law and Policy, 5th ed. (LexisNexis Canada 2017)
HUD is accepting nominations through November 2 for Tribal representatives to serve on its Tribal Intergovernmental Advisory Committee, where they can advise the Department on housing policy.




































 Turtle Talk

You must be logged in to post a comment.